With 2026 now underway, the FDA’s running list of approved companion diagnostics continues to evolve, and the 2025 data is worth a careful look. What follows is an analysis of novel oncology drug approvals from 2020 through 2025, with particular attention to how companion diagnostic co-development has shifted from a common practice to a near-universal expectation.
A decade of steady rates, then a sharp break
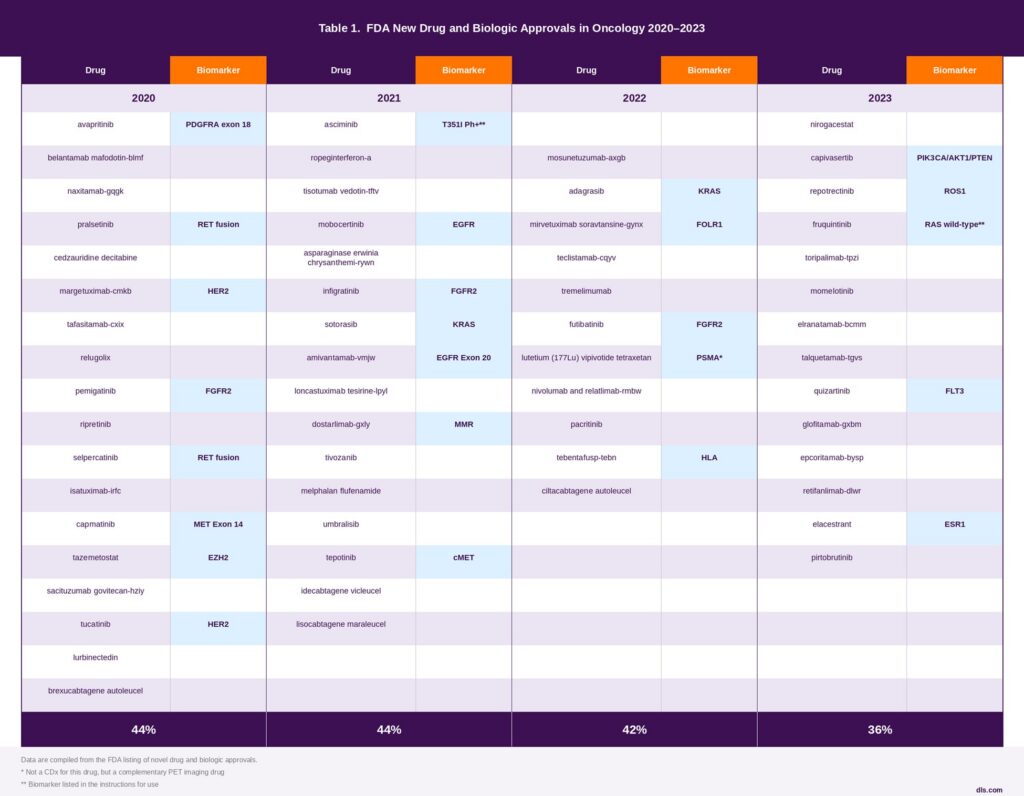
From 2020 through 2023, the share of novel oncology approvals carrying a companion diagnostic or biomarker in the drug label held relatively steady, ranging from 36% to 44%. That consistency suggested CDx integration was standard practice for a meaningful subset of programs, but far from the norm. The reason for this approach is well established, as the use of a predictive biomarker has been shown to roughly double the chances of approval for a novel oncology therapeutic (see here)
Then the data breaks sharply upward.
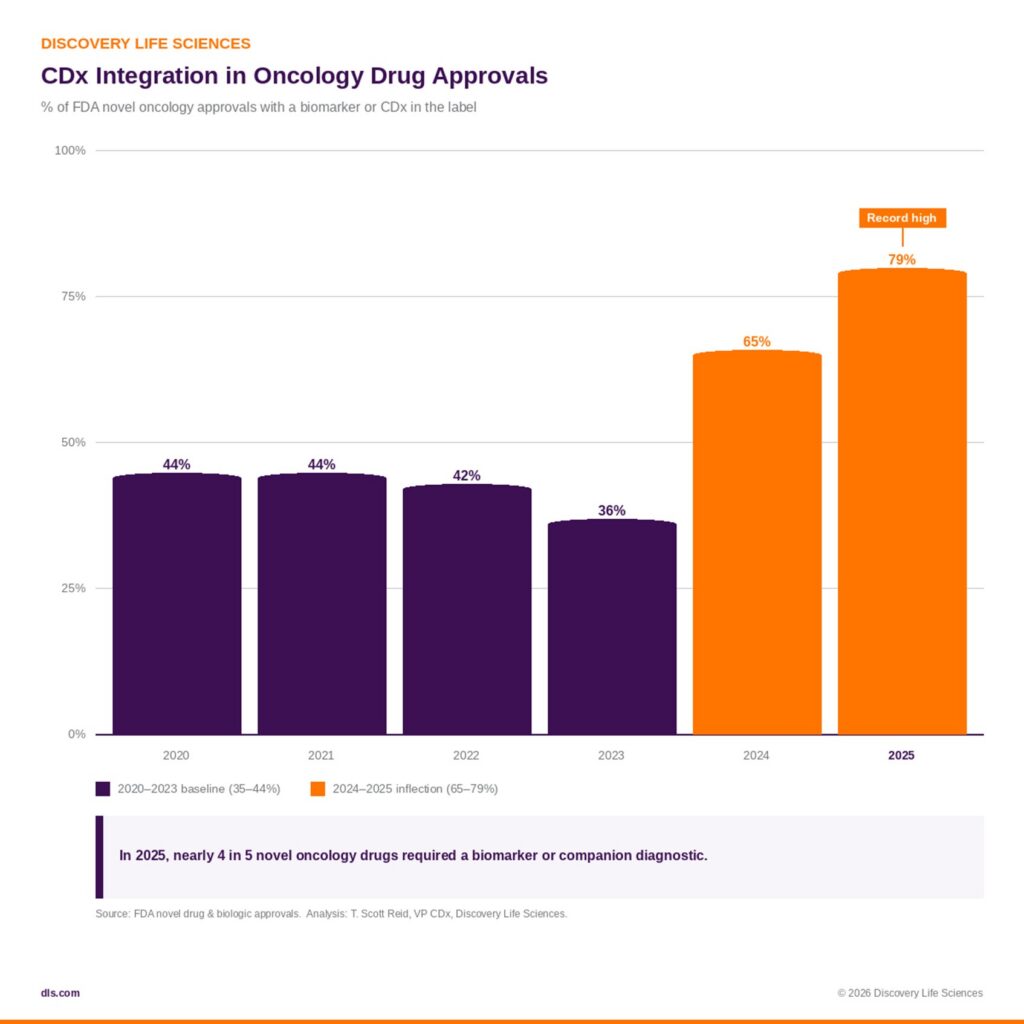
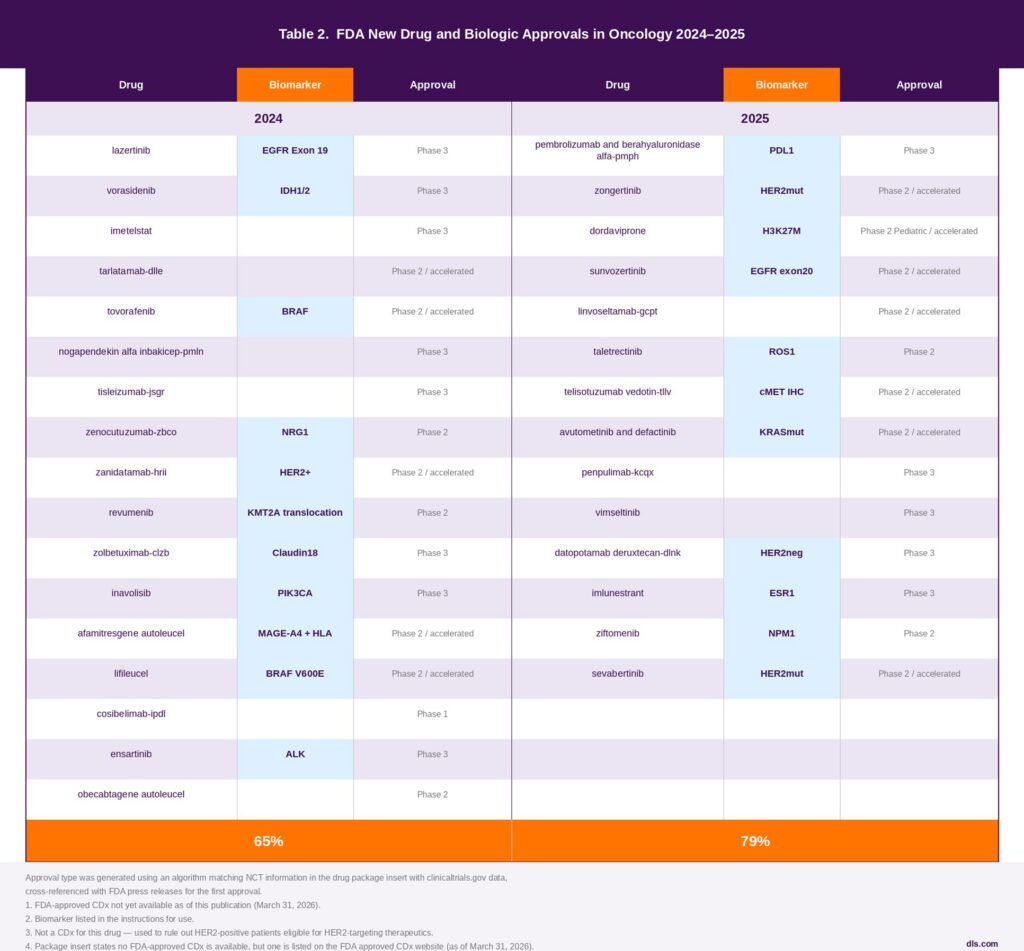
In 2024, 65% of novel oncology approvals included a CDx or biomarker requirement. In 2025, that figure reached 79%. Notably, this trend spans both small molecule and biologic drug classes. CDx-driven development is not an artifact of the ADC wave or large molecule biology alone. Nearly four out of five new oncology drugs approved last year required biomarker-guided patient selection. CDx development is no longer an outlier in oncology drug development. It is the default.
The trend reflects a field-wide response to evidence. Programs using selection biomarkers achieve a likelihood of approval from Phase I more than three times higher than those that do not, according to a landmark analysis of over 9,700 clinical programs by BIO, Informa Pharma Intelligence, and QLS Advisors.¹ In oncology specifically, the advantage is even more pronounced for certain tumor types.² The industry has absorbed this data, and the numbers from 2024 and 2025 show it.
CDx approval routinely lags drug approval, and the gap is widening
Reviewing 2024 and 2025 approvals together, a secondary pattern emerges with significant practical implications: a substantial number of drugs were approved with a biomarker or CDx requirement in the label, but without a corresponding FDA-approved diagnostic test yet available.
Notable examples from 2024 include vorasidenib, tovorafenib, ensartinib, and revumenib. All four carry package insert language stating no FDA-approved CDx is currently available, despite companion diagnostics now appearing on the FDA’s approved CDx list for these agents. These discrepancies reflect the reality that package inserts are not always updated in sync with the FDA’s CDx approvals database. They will be reconciled over time. But the underlying dynamic they expose is real: CDx approval routinely lags drug approval, and that gap appears to be widening.
This is not a regulatory failure. It reflects deliberate flexibility within the agency. With one notable historical exception, ChemGenex’s omacetaxine mepesuccinate, there is no public record of drug approval being withheld solely due to CDx development delays. FDA guidance does call for contemporaneous drug and diagnostic development, but the data confirm that post-marketing commitments are an accepted and commonly used pathway when a drug’s safety and efficacy profile is clear.
Accelerated pathways are reshaping CDx timelines
The most consequential structural shift visible in 2025 is this: the majority of novel oncology approvals came through accelerated or Phase 2-based pathways rather than traditional Phase 3 pivotal studies. This reflects the FDA’s continued movement toward single-arm efficacy studies as the basis for approval in oncology, a direction that carries meaningful downstream consequences for CDx development teams.
When Phase 2 becomes the pivotal study, development and validation of a prototype CDx assay must begin earlier and move faster. Programs that historically had the runway of a Phase 3 to build out their diagnostic strategy now face a compressed timeline, often requiring a functional prototype assay to be deployment-ready before Phase 2 enrollment opens, or in some cases before Phase 1b concludes.
Three conclusions follow this data.
CDx development is now intrinsic to oncology drug development. With close to 80% of novel approvals carrying a biomarker or CDx requirement, a drug program that does not address companion diagnostic strategy early is operating with a meaningful gap in its plan.
Roughly one in three novel oncology approvals in 2024 and 2025 reached the market without a simultaneously approved CDx, meaning post-marketing CDx commitments now represent a substantial and growing portion of the development landscape. Provided diagnostic development is executed competently and commitments are pursued in good faith, pharma companies need not fear CDx approval holding back drug approval or market access.
The demise of the FDA’s LDT rule ensures that lab-developed tests will continue to provide a functioning ecosystem for biomarker-guided patient selection in the absence of an approved CDx, at least in the US market. The absence of an FDA-approved diagnostic is not a barrier to entry in most cases.
What this means in practice
The pressure to compress CDx timelines has become one of the defining operational challenges in oncology drug development. Getting a novel biomarker assay from candidate to clinic-ready within a narrow window, particularly when CDx necessity is not confirmed until Phase 1 is complete, requires both technical agility and operational infrastructure that many sponsors are still building.
Rapid development and validation of prototype CDx assays, often against novel biomarker targets before Phase 1 is complete, is one of the defining operational capabilities that sets Discovery Life Sciences apart in this space. The pressure to compress CDx timelines has become one of the central challenges in oncology drug development, and programs that cannot move from biomarker candidate to clinic-ready assay within a narrow window risk delaying enrollment in pivotal Phase 2 studies. Our team has accumulated meaningful experience navigating exactly this inflection point. In an upcoming post, I will share data from several of those programs.
Footnotes:
¹ Thomas DW, et al. Clinical Development Success Rates and Contributing Factors 2011–2020. BIO, Informa Pharma Intelligence, QLS Advisors; 2021. https://www.bio.org/clinical-development-success-rates-and-contributing-factors-2011-2020
² Parker JL, et al. Does biomarker use in oncology improve clinical trial failure risk? A large-scale analysis. Cancer Medicine. 2021;10(6):1955–1963.

T. Scott Reid, PhD
Scott Reid, PhD, MBA, Vice President and Global Head of Companion Diagnostics at Discovery Life Sciences, brings 25 years of drug development expertise. With experience at SOPHiA Genetics and NeoGenomics, Scott leads innovative CDx solutions for global clinical trials.